
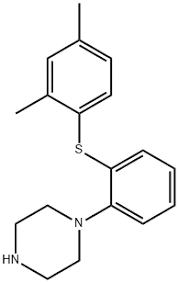
Buy Vortioxetine (Trintellix) Cas 508233-74-7
Buy Vortioxetine (Trintellix) Cas 508233-74-7
Buy Vortioxetine (Trintellix) Cas 508233-74-7
Vortioxetine, sold under the brand names Trintellix (in the US) and Brintellix (in Europe) among others, is an antidepressant medication of the serotonin modulator and stimulator (SMS) class used in the treatment of major depressive disorder.[14][3] Its effectiveness is viewed as similar to that of other antidepressants.[14] It is taken orally.[14]
Common side effects include nausea, dry mouth, diarrhea, constipation, vomiting (3-6% of people), and sexual dysfunction.[14][10] Serious side effects may include suicide in those under the age of 25, serotonin syndrome, bleeding, mania, and SIADH.[14] A withdrawal syndrome may occur if the medication is abruptly stopped or the dose is decreased.[14] Use during pregnancy and breastfeeding is not generally recommended.[15] Vortioxetine’s mechanism of action is not entirely understood, but is believed to be related to increasing serotonin levels and possibly interacting with certain serotonin receptors.[14][16][17]
It was approved for medical use in the United States[18][14][19] and in the European Union in 2013.[11] In 2020, it was the 243rd most commonly prescribed medication in the United States, with more than 1 million prescriptions.[20][21]
Medical uses
Vortioxetine is used as a treatment for major depressive disorder,[14] with its effectiveness shown to be similar to other antidepressants[14][22][23] and its effect size has been described as modest.[24] Vortioxetine may be used when other treatments have failed.[10][25][26][27] A 2017 Cochrane review on vortioxetine determined that its place in the treatment of severe depression is unclear due to low-quality evidence and that more studies comparing vortioxetine to selective serotonin reuptake inhibitors (SSRIs), the typical first-line treatments, are needed.[28] Vortioxetine appears to work in depressed patients with anxiety.[29]
Vortioxetine is also used off label for anxiety.[30] A 2016 review found it was not useful in generalized anxiety disorder at 2.5, 5.0, and 10 mg doses (15 and 20 mg doses were not tested).[31] A 2019 meta-analysis found that vortioxetine did not produce statistically significant results over placebo in the symptoms, quality of life, and remission rates of generalized anxiety disorder, but it was well-tolerated.[32] However, a 2018 meta-analysis supported use and efficacy of vortioxetine for generalized anxiety disorder, though stated that more research was necessary to strengthen the evidence.[33] A 2021 systematic review and meta-analysis concluded that there was uncertainty about the effectiveness of vortioxetine for anxiety due to existing evidence being of very low-quality.[34] In a 2020 network meta-analysis of randomized controlled trials, vortioxetine was among the lowest remission rates for generalized anxiety disorder of the included medications (odds ratio = 1.30 for vortioxetine, range of odds ratios for other agents = 1.13–2.70).[35]
Vortioxetine
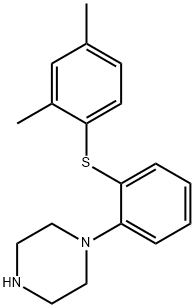
- CAS No.
- 508233-74-7
- Chemical Name:
- Vortioxetine
- Synonyms
- 1-(2-((2,4-DiMethylphenyl)thio)phenyl)piperazine;Vortioxetin;Trintellix (vortioxetine);Votigetin;Votexetine;Lu AA 21004;Vortioxetine;Vortioxetine,98%;1-(2-((2,4-DimethyL;Vortioxetine, >=99%
- CBNumber:
- CB62614395
- Molecular Formula:
- C18H22N2S
- Molecular Weight:
- 298.45
- MDL Number:
- MFCD22380814
- MOL File:
- 508233-74-7.mol
- MSDS File:
- SDS
- TDS File:
- TDS
| Product description | Number | Pack Size | Price |
| Lu AA 21004 | V0200 | 1G | $246 |
| Vortioxetine ≥98% | 30183 | 5mg | $41 |
| Vortioxetine ≥98% | 30183 | 10mg | $75 |
| Vortioxetine ≥98% | 30183 | 25mg | $128 |
| Vortioxetine ≥98% | 30183 | 50mg | $235 |
| More product size | |||
| Melting point | 115-117°C |
|---|---|
| Boiling point | 424.8±45.0 °C(Predicted) |
| Density | 1.16 |
| storage temp. | -20°C Freezer |
| solubility | DMSO (Slightly), Methanol (Slightly) |
| pka | 8.85±0.10(Predicted) |
| form | Solid |
| color | White to Off-White |
| InChI | InChI=1S/C18H22N2S/c1-14-7-8-17(15(2)13-14)21-18-6-4-3-5-16(18)20-11-9-19-10-12-20/h3-8,13,19H,9-12H2,1-2H3 |
| InChIKey | YQNWZWMKLDQSAC-UHFFFAOYSA-N |
| SMILES | N1(C2=CC=CC=C2SC2=CC=C(C)C=C2C)CCNCC1 |
| FDA UNII | 3O2K1S3WQV |
| ATC code | N06AX26 |
| NACRES | NA.21 |
SAFETY
Risk and Safety Statements
| Symbol(GHS) |  GHS08 |
|---|---|
| Signal word | Warning |
| Hazard statements | H371-H373-H361 |
| Precautionary statements | P260-P314-P501-P201-P202-P281-P308+P313-P405-P501-P260-P264-P270-P309+P311-P405-P501 |
| Hazardous Substances Data | 508233-74-7(Hazardous Substances Data) |
Vortioxetine price More Price(72)
| Manufacturer | Product number | Product description | CAS number | Packaging | Price | Updated | Buy |
|---|---|---|---|---|---|---|---|
| TCI Chemical | V0200 | Lu AA 21004 | 508233-74-7 | 1G | $246 | 2026-04-30 | Buy |
| Cayman Chemical | 30183 | Vortioxetine ≥98% | 508233-74-7 | 5mg | $41 | 2026-04-30 | Buy |
| Cayman Chemical | 30183 | Vortioxetine ≥98% | 508233-74-7 | 10mg | $75 | 2026-04-30 | Buy |
| Cayman Chemical | 30183 | Vortioxetine ≥98% | 508233-74-7 | 25mg | $128 | 2026-04-30 | Buy |
| Cayman Chemical | 30183 | Vortioxetine ≥98% | 508233-74-7 | 50mg | $235 | 2026-04-30 | Buy |
Vortioxetine Chemical Properties,Uses,Production
Curative for Major Depression Disorder
Vortioxetine is a new drug for treating depression, jointly developed and researched by the Danish Lundbeck (Lundbeck) and Japanese Takeda. In September 30, 2013, It is approved by the U.S. Food and Drug Administration (FDA) to enter into market with the brand name of Brintellix, for Major Depression Disorder (MDD) treatment.
In October 2013, the European Medicines Agency (EMA)’s subordinate agency: Committee for Medicinal Products for Human Use (CHMP) recommended that vortioxetine for the treatment of severe depression should be licensed in the European market and be launched into the European market in January 2014.
MDD features mood changes and a series of other symptoms, which have a great impact on the patient’s ability to work, sleep, study, eat and enjoy the current happiness. Depressive symptoms can recur many times in life, but some patients may experience only once.
Vortioxetine, mainly by increasing the concentration of serotonin (5-HT) in the central nervous system (CNS), exerts antidepressant effects. Compared with other selective serotonin reuptake inhibitors (SSRIS) or serotonin-norepinephrine reuptake inhibitors (SNRIS), vortioxetine almost has no effect on norepinephrine and dopamine neurons. A number of clinical trials have demonstrated the efficacy, safety and tolerability of vortioxetine in the treatment of MDD.
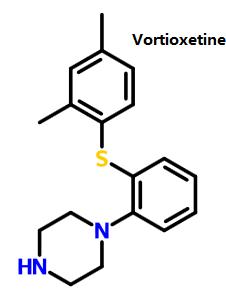
Figure 1 shows the structure of vortioxetine.
Mechanism of Action
Vortioxetine is a small molecule piperazine sulfide. WHO w classifies it as antidepressants (N06A). The drug classification system of European Pharmaceutical Market Research Association (EPhMRA) classifies it as hypnotic / sedative drugs (N5B), antidepressants and mood stabilizers (N6A). Currently, depression is thought to be associated with a decrease in 5-HT activity, and decreased activity of norepinephrine (NE) and dopamine (DA) is thought to be associated with depression.
Vortioxetine is a potent serotonin reuptake inhibitor. In human body it has high affinity with serotonin trans-porter (Ki=1.6 nmol – L – 1). But it almost has no affinity with norepinephrine transporter (Ki=113nmol – L-1) and dopamine transporter (Ki= 1000nmol – L – 1). At the same time, it is also a 5-HT1A receptor agonist and 5-HT1B receptor partial agonist, 5-HT1D, 5-HT3 and 5-HT7 receptor antagonist and 5-HT uptake inhibitor. Animal studies have shown that in rats, vinpocetine through interaction on these receptors, will increase depression related brain regions — the level of the ventral hippocampus, prefrontal cortex extracellular serotonin , dopamine, norepinephrine, acetylcholine and histamine, at the same time it is also regulating the function of y -GABA (γ-aminobutyric acid) and glutamatergic neuron, thus exerting the effect of antidepressant.
Pharmacokinetics
The relative molecular weight of vortioxetine is small, and the plasma protein binding rate is 98 percent, which is not related to plasma concentration. It is widely distributed outside the cell and the apparent distribution volume is about 2600 L. Daily oral administration is 2.5 ~ 60mg, showing the linear pharmacokinetic characteristics in proportion to dosage of administration. Bioavailability is 75 percent and generally after 2 weeks of taking vortioxetine, its concentration will be stable in blood. Cmax is 7 to 11 hours. Vortioxetine is metabolized mainly by oxidation and glucuronidation . After a single oral administration of the radioisotope labeled vortioxetine, about 59 percent of it is excreted through the urine, and about 26 percent were excreted through the feces. There was almost no original vortioxetine 48 hours after administration of the drug. The complete metabolism in body requires about 66 hours. The oxidation is mainly completed through cytochrome P450 enzyme (CYP). The involved CYP includes CYP3A4/5, CYP2C19, CYP2C9, CYP2A6, CYP2C8, CYP2B6 and CYP2D6. Among them, CYP2D6 is the key enzyme which catalyzes and produces the main metabolite of duloxetine carboxylic acid. The drug concentration of CYP2D6 in the plasma with slow metabolism is twice higher than that of CYP2D6 in the plasma with the fast metabolism.
Drug Interaction
- In the different experiment and researches using healthy volunteers as subjects, vortioxetine will be co-administered respectively with CYP2D6 inhibitor bupropion, CYP2C9/CYP2C19/CYP3A inhibitor fluconazole or CYP3A/ permeability glycoprotein (P-gp) inhibitor ketoconazole. The vortioxetine’s bioavailability will increase. Therefore when vortioxetine and strong CYP2D6 inhibitors (such as bupropion, fluoxetine, paroxetine and quinidine) are co-administered, the dosage should be halved.
- When vortioxetine and strong CYP inducers (rifampicin) are co-administered, its bioavailability will be reduced. Therefore when vortioxetine is co-administered with rifampicin or other strong CYP inducers (such as carbamazepine, Phenytoin sodium), the dosage should be increased, but the maximum dosage should not be three times higher than the normal dose.
- In addition, the use of 5-HT drugs itself is a risk factors of incurring abnormal bleeding. Therefore when vortioxetine is co-administered with aspirin, nonsteroidal anti-inflammatory drugs or other drugs affecting blood coagulation, special attention should be drawn to the abnormal bleeding of patients.
- Considering the functional mechanism of vortioxetine and potential toxicity of serotonin, so when it is co-administered with other drugs affecting 5-HT neurotransmitter systems (such as SSRIs, SNRIs, and triptans, buspirone, tramadol and tryptophan products), lt is likely to occur 5-HT syndrome. Therefore, close attention should be paid to the risk of 5-HT syndrome when it is used in combination with such drug. Once the 5-HT syndrome occurs, all such drugs should be discontinued immediately.
- Similar to the above reasons, monoamine oxidase inhibitors (MAOIs) are prohibited from being used in combination with MAOIs. MAOIs can not be administered within 21d after discontinuation of vortioxetine, and vortioxetine can not be administered within 14d after discontinuation of MAOIs. Because the combination of both will increase the risk of 5-HT syndrome in patients.
Synthesis
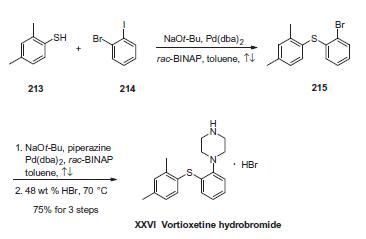
- 2,4-dimethyl-1- iodo-benzene reacts with 2- bromophenyl thiophenol and Bis(dibenzylidene acetone)palladium, under sodium tert-butoxide’s catalysis to generate vortioxetine
- 2,4- dimethyl thiophenol and 2- bromo benzene and piperazine(1-BOC-piperazine) react under the catalysis of Bis(dibenzylidene acetone)palladium , 1, 1′- linked naphthalene -2, 2′- bis diphenyl phosphine and sodium tert-butoxide to generate vortioxetine.
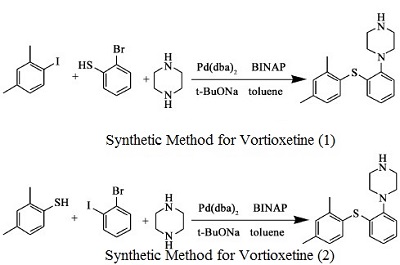 Figure 1 is a chemical reaction diagram for the synthesis of vortioxetine.
Description
In September 2013, vortioxetine (also known as Lu AA21004) was approved in the United States for the treatment of major depressive disorder (MDD). Vortioxetine was discovered from a designed multiple ligand approach to identifying an antidepressant agent that combined SERT inhibition with 5-HT1A agonism to more rapidly desensitize 5-HT1A receptors and 5-HT3A antagonism to improve mood and cognitive function. Vortioxetine has a human SERT IC50=5.4 nM, an EC50=200 nM as a human 5-HT1A receptor agonist (efficacy=96%; Ki=39 nM), and an IC50=12 nM as a human 5-HT3A receptor antagonist (Ki=3.7 nM). It has weak inhibition of the dopamine and norepinephrine transporters, but high affinity for the human β1-noradrenergic receptor (Ki=46 nM), human 5-HT1B receptor (Ki=33 nM, partial agonist), and the human 5-HT-7 receptor (Ki=19 nM, antagonist).
Originator
Lundbeck (Denmark)
History
Vortioxetine was invented by scientists at Lundbeck who reported the rationale and synthesis for the drug (then called Lu AA21004) in a 2011 paper. Takeda and Lundbeck Announce the U.S. Submission of a New Drug Application for Vortioxetine, an Investigational Drug for the Treatment of Major Depressive Disorder on Oct 1, 2012. Vortioxetine, which was approved by the Food and Drug Administration (FDA) on September 30, 2013, for treatment of major depressive disorder (MDD) , and Brintellix (vortioxetine) Renamed Trintellix (vortioxetine) in U.S. to Avoid Name Confusion.
Uses
Vortioxetine can be used in biological study of effectiveness of long term vortioxetine treatment of patients with major depressive disorder.
Definition
ChEBI: An N-arylpiperazine in which the aryl group is specified as 2-[(2,4-dimethylphenyl)sulfanyl]phenyl. Used (as its hydrobromide salt) for treatment of major depressive disorder.
brand name
Brintellix
Clinical Use
Antidepressant
Synthesis
The sequence involves iterative palladium-catalyzed carbon¨C heteroatom bond formations, the first establishing the thioethereal bond between commercially available thiol (213) and o-iodobromobenzene (214) employing conditions described by Schopfer and Schlapbach. Next, Buchwald¨CHartwig conditions were employed to establish the piperazine linkage, and this was followed by subjection to warm hydrobromic acid to furnish vortioxetine hydrobromide (XXVI) in 75% yield across the entire three-step sequence.
in vitro
vortioxetine (lu aa21004) was the lead compound, displaying high affinity for recombinant human 5-ht1a (ki = 15 nm), 5-ht1b (ki = 33 nm), 5-ht3a (ki = 3.7 nm), 5-ht7 (ki = 19 nm), and noradrenergic β1 (ki = 46 nm) receptors, and sert (ki = 1.6 nm). vortioxetine displayed antagonistic properties at 5-ht3a and 5-ht7 receptors, partial agonist properties at 5-ht1b receptors, agonistic properties at 5-ht1a receptors, and potent inhibition of sert [1].
in vivo
in conscious rats, vortioxetine significantly increased extracellular 5-ht levels in the brain after acute and 3 days of treatment. following the 3-day treatment (5 or 10 mg/kg/day) sert occupancies were only 43% and 57%, respectively [1].
target
5-HT3 receptor
Drug interactions
Potentially hazardous interactions with other drugs
Antibacterials: avoid with linezolid; concentration reduced by rifampicin – consider increasing vortioxetine dose.
Antidepressants: possible increased risk of convulsions with SSRIs and, tricyclics; avoid with moclobemide; increased risk of hypertension and CNS excitation with MAOIs – avoid.
Antiepileptics: concentration possibly reduced by carbamazepine, fosphenytoin and phenytoin – consider increasing vortioxetine dose.
Antimalarials: possible increased risk of convulsions with mefloquine; avoid with artemether with lumefantrine and artenimol with piperaquine.
Antipsychotics: possible increased risk of convulsions with butyrophenones, phenothiazines and thioxanthenes.
Dopaminergics: risk of CNS excitation and hypertension with rasagiline and selegiline.
Metabolism
Vortioxetine is extensively metabolised in the liver, mainly by oxidation catalysed by CYP2D6 and to a minor extent CYP3A4/5 and CYP2C9, and subsequent glucuronic acid conjugation. The major metabolite of vortioxetine is pharmacologically inactive.
Approximately two thirds of the inactive vortioxetine metabolites are excreted in the urine and approximately one third in the faeces. Only negligible amounts of vortioxetine are excreted in the faeces.
| Targets |
sPLA2 ( Ki = 15 nM ); 5-HT3A Receptor ( Ki = 3.7 nM ); Human 5-HT7 Receptor ( Ki = 19 nM ); SERT ( Ki = 1.6 nM )
In vitro activity: Vortioxetine (Compound 5m) is a multimodal serotonergic agent that inhibits SERT with values of 1.6 nM, 33 nM, 3.7 nM, 19 nM, and 5-HT1A, 5-HT1B, and 5-HT7 receptors, respectively. Vortioxetine exhibits strong suppression of SERT, partial agonist characteristics at 5-HT1B and 5-HT1A receptors, antagonistic properties at 5-HT3A and 5-HT7 receptors, and agonistic properties at 5-HT1A receptors[1]. Using a whole-cell cAMP-based assay, vortioxetine is a partial h5-HT1B receptor agonist with an EC50 of 460 nM and intrinsic activity of 22%. In vitro whole-cell cAMP assay, vortioxetine binds to the r5-HT7 receptor with a Ki value of 200 nM and is a functional antagonist at the r5-HT7 receptor with an IC50 of 2 μM[5]. |
|---|---|
| ln Vitro |
In vitro activity: Vortioxetine (Compound 5m) is a multimodal serotonergic agent that inhibits SERT with values of 1.6 nM, 33 nM, 3.7 nM, 19 nM, and 5-HT1A, 5-HT1B, and 5-HT7 receptors, respectively. Vortioxetine exhibits strong suppression of SERT, partial agonist characteristics at 5-HT1B and 5-HT1A receptors, antagonistic properties at 5-HT3A and 5-HT7 receptors, and agonistic properties at 5-HT1A receptors[1]. Using a whole-cell cAMP-based assay, vortioxetine is a partial h5-HT1B receptor agonist with an EC50 of 460 nM and intrinsic activity of 22%. In vitro whole-cell cAMP assay, vortioxetine binds to the r5-HT7 receptor with a Ki value of 200 nM and is a functional antagonist at the r5-HT7 receptor with an IC50 of 2 μM[5].
|
| ln Vivo |
Vortioxetine (Lu AA21004) is a 5-HT3 receptor antagonist that binds to the r5-HT1B receptor and rSERT (ED50 = 3.2 and 0.4 mg/kg, respectively) when administered subcutaneously[6]. After 21 days of treatment, vortioxetine dramatically boosts immature granule cell maturation in the sub granular zone of the dentate gyrus of the hippocampus as well as cell survival and proliferation[3]. Cognitive or psychomotor impairment is not brought on by vortioxetine[4].
Acute oral administration of Vortioxetine (5 mg/kg, 1h pre-test) to BALB/cJ mice produced anxiolytic-like effects in the open field test, increasing time spent in the center (p<0.05), number of center entries (p<0.05), and distance traveled in the center (p<0.05), comparable to diazepam (1.5 mg/kg). The 10 mg/kg dose was ineffective. [2] |
| Enzyme Assay |
Vortioxetine (Compound 5m) is a multimodal serotonergic agent that inhibits SERT with values of 1.6 nM, 33 nM, 3.7 nM, 19 nM, and 5-HT1A, 5-HT1B, and 5-HT7 receptors, respectively. Vortioxetine exhibits strong suppression of SERT as well as antagonistic effects at 5-HT3A and 5-HT7 receptors, partial agonist effects at 5-HT1B receptors, and agonistic effects at 5-HT1A receptors.
Compound 5m (Lu AA21004) was the lead compound, displaying high affinity for recombinant human 5-HT(1A) (K(i) = 15 nM), 5-HT(1B) (K(i) = 33 nM), 5-HT(3A) (K(i) = 3.7 nM), 5-HT(7) (K(i) = 19 nM), and noradrenergic β(1) (K(i) = 46 nM) receptors, and SERT (K(i) = 1.6 nM). Compound 5m displayed antagonistic properties at 5-HT(3A) and 5-HT(7) receptors, partial agonist properties at 5-HT(1B) receptors, agonistic properties at 5-HT(1A) receptors, and potent inhibition of SERT.[1] Ex vivo SERT and 5-HT3 receptor occupancy assays[2] |
| Cell Assay |
Vortioxetine is a partial h5-HT1B receptor agonist that, in a whole-cell cAMP-based assay, has an EC50 of 460 nM and an intrinsic activity of 22%. In vitro whole-cell cAMP assay, vortioxetine binds to the r5-HT7 receptor with a Kivalue of 200 nM and is a functional antagonist at the r5-HT7 receptor with an IC50 of 2 μM.
Assessment of SERT occupancy[2] Assessment of 5-HT3 receptor occupancy[2] |
| Animal Protocol |
Dissolved in 10% hydroxypropyl-β-cyclodextrin; 10 mg/kg; s.c. administrationRats Acute studies[2]
Three doses of vortioxetine (2.5, 5 and 10 mg/kg, free base dissolved in 10% β-cyclodextrin, oral gavage, p.o.,) were used in the OF test, the NSF test and the FST. The effects of vortioxetine were compared to the vehicle control group (10% β-cyclodextrin) and also to a fluoxetine- (18 mg/kg p.o., (David et al., 2007)) and a diazepam-treated group (1.5 mg/kg, s.c. (David et al., 2007)). All doses were corrected for the weight of the salt. All treatments were administered 1 h before testing. Chronic studies[2] For acute behavioral studies, Vortioxetine (free base) was dissolved in 10% β-cyclodextrin and administered orally (p.o.) by gavage at doses of 2.5, 5, or 10 mg/kg. Behavioral tests (open field, forced swim test, novelty-suppressed feeding) were conducted 1 hour after administration. Control groups received vehicle (10% β-cyclodextrin), fluoxetine (18 mg/kg p.o.), or diazepam (1.5 mg/kg s.c.). [2] |
| ADME/Pharmacokinetics |
Absorption, Distribution and Excretion
Following administration, the maximum plasma concentration (Cmax) of vortioxetine was reached within 7 to 11 hours. The absolute bioavailability was 75%. No effect of food on pharmacokinetics was observed. Following a single oral administration of [14C]-labeled vortioxetine, approximately 59% and 26% of the administered radioactivity, respectively, were recovered as metabolites in urine and feces. The amount of unmetabolized vortioxetine excreted in urine within 48 hours was negligible. The apparent volume of distribution of vortioxetine is approximately 2600 liters, indicating its extensive extravascular distribution. /Breast Milk/ It is unclear whether vortioxetine is present in human breast milk. Vortioxetine is present in the breast milk of lactating rats. Vortioxetine is a novel multimodal drug for the treatment of major depressive disorder, exhibiting high affinity for multiple different serotonergic targets in the central nervous system. We report the (11)C labeling of vortioxetine with (11)C-MeI using the Suzuki conjugation protocol, which allows for the presence of unprotected amino groups. Preliminary evaluation of (11)C-vortioxetine in Danish Landrace pigs showed rapid uptake and distribution in the brain, consistent with its pharmacological profile, although unexpectedly high binding was also observed in the cerebellum. (11)C-vortioxetine exhibited slow tracer kinetics, reaching peak uptake after 60 minutes, with limited clearance from the brain. Further research is needed, but this radioligand could be a valuable tool for elucidating the clinical efficacy of vortioxetine. Vortioxetine and its related substances are primarily excreted via feces in mice (84%), rats (69%), and dogs (59% and 65% in two independent studies, respectively), while in humans, it is primarily excreted via urine (59%), with less fecal excretion (26%). In excretion studies, the recovery rates of vortioxetine and its related compounds in rodents were close to 100%. Excretion in dogs and humans was slower, with recoveries of approximately 90% and 85% after 168 hours and 360 hours, respectively. This study aimed to characterize the pharmacokinetics of vortioxetine and assess the effects of intrinsic and extrinsic factors on healthy individuals. Data from 26 clinical pharmacology studies were compiled. A total of 21,758 measurable plasma concentrations of vortioxetine were collected from 887 subjects with corresponding demographic characteristics. Dosage ranges were 2.5 to 75 mg (single dose) and 2.5 to 60 mg (once daily, multiple doses). The pharmacokinetic profile of vortioxetine best fit a two-compartment model, which includes first-order absorption, lag time, and linear elimination, and accounts for inter-individual error terms for the absorption rate constant, oral clearance, and central volume of distribution. The population mean oral clearance was 32.7 L/hr, and the population mean central volume of distribution was 1.97 × 10³ L. The mean elimination half-life was 65.8 hours. Statistically significant covariate-parameter relationships were found between CYP2D6-inferred metabolic status (ultra-rapid metabolizer, rapid metabolizer, intermediate metabolizer, or slow metabolizer) and age with oral clearance, and between height and central volume of distribution. For individuals with lower CYP2D6 metabolic capacity, the CL/F value was approximately 50% of that of individuals with higher CYP2D6 metabolic capacity. Height had a small effect on V2/F value, and age had a small effect on CL/F value, which was not clinically significant. The final model was proven to be reliable, stable, and predictive. We developed a reliable, stable, and predictive pharmacokinetic model to characterize the pharmacokinetic properties of vortioxetine in healthy individuals. For more complete data on the absorption, distribution, and excretion of vortioxetine (10 parameters), please visit the HSDB record page. Metabolism/Metabolites Vortioxetine is extensively metabolized primarily through oxidation by cytochrome P450 isoenzymes CYP2D6, CYP3A4/5, CYP2C19, CYP2C9, CYP2A6, CYP2C8, and CYP2B6, followed by glucuronide conjugation. CYP2D6 is the major enzyme catalyzing the metabolism of vortioxetine into a pharmacologically inactive carboxylic acid metabolite. The plasma concentration of vortioxetine is approximately twice that of individuals with low CYP2D6 metabolic capacity compared to those with high metabolic capacity. Vortioxetine is extensively metabolized primarily through oxidation by cytochrome P450 isoenzymes CYP2D6, CYP3A4/5, CYP2C19, CYP2C9, CYP2A6, CYP2C8, and CYP2B6, followed by glucuronide conjugation. CYP2D6 is the major enzyme catalyzing the metabolism of vortioxetine into a pharmacologically inactive carboxylic acid metabolite. The plasma concentration of vortioxetine is approximately twice that of individuals with low CYP2D6 metabolic capacity compared to those with high metabolic capacity. All metabolites detected in human hepatocytes, except for the monohydroxyvortioxetine glucuronide conjugate, were found in dogs, mice, and rats (plasma and/or urine), while the monohydroxyvortioxetine glucuronide conjugate was not found in mice and rats. Among all tested species, the metabolite profile of rabbit hepatocytes appears to be the closest to that of human hepatocytes. The mean terminal half-life is approximately 66 hours. The absolute oral bioavailability in rats, dogs, and patients is approximately 10%, 48%, and 75%, respectively, with corresponding terminal elimination half-lives of 3.0 hours, 7.9 hours, and 66 hours. …Data from 26 clinical pharmacology studies are summarized. A total of 21,758 quantifiable plasma concentrations of vortioxetine were collected from 887 subjects with corresponding demographic characteristics. The dosage range was 2.5 to 75 mg (single dose) and 2.5 to 60 mg (once daily multiple doses). …The mean elimination half-life was 65.8 hours. The mean elimination half-life and oral clearance were 66 hours and 33 L/hour, respectively. The half-life of vortioxetine in rats was approximately 3.2 hours, and there were no active metabolites at its target site. [2] |
| Toxicity/Toxicokinetics |
Toxicity Summary
Identification and Uses: Vortioxetine is a white to micron-colored powder, formulated as film-coated tablets. It is used to treat major depressive disorder in adults. Human Exposure and Toxicity: Clinical experience with human overdose of vortioxetine is limited. In premarketing clinical studies, overdose cases were limited to patients who accidentally or intentionally ingested no more than 40 mg of vortioxetine. The maximum single test dose for male subjects was 75 mg. Administration of vortioxetine in the dose range of 40 to 75 mg was associated with an increased incidence of nausea, dizziness, diarrhea, abdominal discomfort, generalized itching, drowsiness, and flushing. Toxicity can also occur at therapeutic dose levels of vortioxetine. It has been reported that the use of serotonergic antidepressants alone (including vortioxetine) can cause life-threatening serotonin syndrome, especially when used concurrently with other serotonergic drugs (including serotonin (5-HT) type 1 receptor agonists (“triptans”), tricyclic antidepressants, buspirone, fentanyl, lithium, tramadol, tryptophan, and St. John’s wort) and drugs that impair serotonin metabolism (particularly monoamine oxidase (MAO) inhibitors, including those used to treat mental illness and others such as linezolid and methylene blue). Clinical manifestations of serotonin syndrome may include altered mental status (e.g., agitation, hallucinations, delirium, and coma), autonomic dysfunction (e.g., tachycardia, blood pressure fluctuations, dizziness, excessive sweating, flushing, and high fever), neuromuscular symptoms (e.g., tremor, rigidity, myoclonus, hyperreflexia, and incoordination), seizures, and/or gastrointestinal symptoms (e.g., nausea, vomiting, and diarrhea). Concomitant or recent (i.e., within 2 weeks) use of monoamine oxidase inhibitors (MAO inhibitors) for the treatment of mental illness is contraindicated. Use of MAO inhibitors for the treatment of mental illness within 3 weeks of discontinuing vortioxetine is also contraindicated. Furthermore, patients receiving other MAO inhibitors (such as linezolid or intravenous methylene blue) should not begin taking vortioxetine. If concomitant use of vortioxetine and other serotonergic drugs is clinically necessary, patients should be informed of the potential increased risk of serotonin syndrome, especially at the beginning of treatment or when increasing the dose. Short-term studies have shown that antidepressants increase the risk of suicidal ideation and behavior in children, adolescents, and young adults. These studies did not show an increased risk of suicidal ideation and behavior in patients over 24 years of age; there was a trend towards a reduced risk in patients 65 years of age and older. Vortioxetine did not show genotoxicity in in vitro human lymphocyte chromosome aberration assays. Animal studies: The acute single-dose toxicity of vortioxetine is relatively low, with maximum tolerated doses (MTDs) of 300 mg/kg in mice and 500 mg/kg in rats. Rats administered 500 mg/kg showed clinical symptoms including marked sensitivity to touch and disturbances, rapid breathing, and brown staining around the nose. Mice administered 200 and 300 mg/kg showed tremors, tactile sensitivity, half-closed eyes, and decreased activity; those administered 400 and 500 mg/kg showed rapid breathing, coarse breath sounds and/or dyspnea, incoordination, unsteady gait, tilting, salivation, and hyperactivity. Administering vortioxetine (200 mg/kg) twice at one-hour intervals resulted in clinical symptoms, including seizures, ultimately leading to death. In carcinogenicity studies, mice and rats were orally administered vortioxetine at doses up to 50 and 100 mg/kg/day in males and females, respectively, and up to 40 and 80 mg/kg/day in males and females, respectively, for two years. The incidence of benign rectal polypoid adenomas was significantly higher in female rats than in male rats. These polypoid adenomas are thought to be associated with inflammation and hyperplasia and may be caused by interactions of excipient components in the formulation used in the study. This phenomenon was not observed in male rats. In mice, vortioxetine was not carcinogenic in either male or female mice. Administration of vortioxetine during pregnancy in rats and rabbits resulted in developmental delay. Rats given vortioxetine during pregnancy and lactation also showed developmental delay after birth. No teratogenic effects were observed in rats or rabbits given vortioxetine during organogenesis. Administration of vortioxetine to rats at doses up to 120 mg/kg/day had no effect on the fertility of either male or female rats. Vortioxetine did not show genotoxicity in the in vitro bacterial reverse mutation assay (Ames test) and the in vivo rat bone marrow micronucleus assay. Hepatotoxicity Use during pregnancy and lactation Protein Binding Interactions Compared to excipients, long-term administration of vortioxetine (5 or 20 mg/kg/day, orally, for 14 or 21 days) did not result in a significant decrease in body weight in mice. Control. [2] |
| References |
|
| Additional Infomation |
Therapeutic Uses
Anti-anxiety medication; 5-HT1 receptor agonist; 5-HT1 receptor antagonist; 5-HT3 receptor antagonist; serotonin reuptake inhibitor. /Clinical Trials/ ClinicalTrials.gov is a registry and results database that indexes human clinical studies funded by public and private institutions worldwide. The website is maintained by the National Library of Medicine (NLM) and the National Institutes of Health (NIH). Each record on ClinicalTrials.gov includes a summary of the study protocol, including: the disease or condition; the intervention (e.g., the medical product, behavior, or procedure under investigation); the study title, description, and design; participation requirements (eligibility criteria); the location of the study; contact information for the study location; and links to relevant information from other health websites, such as the NLM’s MedlinePlus (which provides patient health information) and PubMed (which provides citations and abstracts of academic articles in the medical field). Vortioxetine is indexed in the database. Brintellix is indicated for the treatment of major depressive disorder (MDD). The efficacy of Brintellix has been demonstrated in six studies lasting 6 to 8 weeks (including one study in older adults) and one maintenance treatment study in adults. /Included on US product label/ Drug Warnings Pharmacodynamics Vortioxetine (Lu AA21004) is a novel investigational multimodal antidepressant. [2] |
| Molecular Formula |
C18H22N2S
|
|
|---|---|---|
| Molecular Weight |
298.45
|
|
| Exact Mass |
298.15
|
|
| Elemental Analysis |
C, 72.44; H, 7.43; N, 9.39; S, 10.74
|
|
| CAS # |
508233-74-7
|
|
| Related CAS # |
Vortioxetine hydrobromide; 960203-27-4; Vortioxetine-d8; 2140316-62-5; 1253056-29-9 (lactate)
|
|
| PubChem CID |
9966051
|
|
| Appearance |
Light yellow to yellow solid powder
|
|
| Density |
1.2±0.1 g/cm3
|
|
| Boiling Point |
424.8±45.0 °C at 760 mmHg
|
|
| Flash Point |
210.7±28.7 °C
|
|
| Vapour Pressure |
0.0±1.0 mmHg at 25°C
|
|
| Index of Refraction |
1.643
|
|
| LogP |
4.26
|
|
| Hydrogen Bond Donor Count |
1
|
|
| Hydrogen Bond Acceptor Count |
3
|
|
| Rotatable Bond Count |
3
|
|
| Heavy Atom Count |
21
|
|
| Complexity |
316
|
|
| Defined Atom Stereocenter Count |
0
|
|
| SMILES |
S(C1C([H])=C([H])C(C([H])([H])[H])=C([H])C=1C([H])([H])[H])C1=C([H])C([H])=C([H])C([H])=C1N1C([H])([H])C([H])([H])N([H])C([H])([H])C1([H])[H]
|
|
| InChi Key |
YQNWZWMKLDQSAC-UHFFFAOYSA-N
|
|
| InChi Code |
InChI=1S/C18H22N2S/c1-14-7-8-17(15(2)13-14)21-18-6-4-3-5-16(18)20-11-9-19-10-12-20/h3-8,13,19H,9-12H2,1-2H3
|
|
| Chemical Name |
1-[2-(2,4-dimethylphenyl)sulfanylphenyl]piperazine
|
|
| Synonyms |
|
|
| HS Tariff Code |
2934.99.9001
|
|
| Storage |
Powder -20°C 3 years 4°C 2 years In solvent -80°C 6 months -20°C 1 month |
|
| Shipping Condition |
Room temperature (This product is stable at ambient temperature for a few days during ordinary shipping and time spent in Customs)
|
Vortioxetine Preparation Products And Raw materials
-
Vortioxetine | 508233-74-7 – ChemicalBook
Vortioxetine (CAS 508233-74-7) information, including chemical properties, …
-
Boiling point: 424.8±45.0 °C (Predicted)
-
Melting point: 115-117°C
-
Density: 1.16
-
storage temp.: 20°C Freezer
-
-
Vortioxetine, ≥99% | CAS 508233-74-7 | Lancrix Chemicals
Buy Vortioxetine, ≥99% CAS: 508233-74-7 from Lancrix Chemicals, Synonyms:Lu AA21004
-
Vortioxetine | Cas no:508233-74-7 | Svaklifesciences
Vortioxetine, Cas no:508233-74-7 1- [2- [ (2,4-Dimethylphenyl)thio]phenyl]piperazine ; 1- [2- (2,4 …
-
Vortioxetine | CAS No: 508233-74-7 – aquigenbio.com
May 21, 2024 · Buy high quality Vortioxetine, CAS No: 508233-74-7 from AquigenBio, the leading Pharmaceutical Impurities …
-
CAS NO: 508233-74-7
-
Mol.F.: C18H22N2S
-
CAT NO: AQ-V000109
-
Category: Impurity Standards
-
-
Vortioxetine | 508233-74-7
Buy Vortioxetine CAS No-508233-74-7 Online from Chemicea Pharma, Manufacturer and Exporter of Vortioxetine
Vortioxetine | CAS 508233-74-7 | Cayman Chemical | Biomol.com
Buy Vortioxetine, CAS: 508233-74-7, item number: Cay30183-5 from Cayman Chemical at Biomol!
-
Vortioxetine | CAS No- 508233-74-7 | Simson Pharma Limited
Buy Vortioxetine CAS No- 508233-74-7, a high quality product from Simson Pharma Limited, a Leading Manufacturer and Exporter …
Vortioxetine (AA21004) | Serotonin Transporter Inhibitor | CAS 508233 …
The FDA authorized vortioxetine, an atypical antidepressant, in 2013 for the treatment of major depressive disorder (MDD) in adults. …
Vortioxetine | 508233-74-7 | SynZeal
Buy high-quality Vortioxetine from SynZeal. Vortioxetine Reference Standard is supplied with COA and analytical data. CAS No. …
-
Vortioxetine | CAS No- 508233-74-7 | Simson Pharma Limited
Buy High-Quality Vortioxetine Reference Standards, Impurity Standards, Metabolites, Analytical Standards, Pharmacopoeial & Non …
Reviews
There are no reviews yet.