
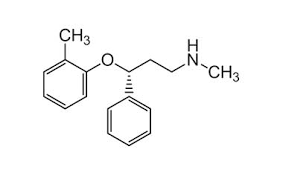
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Atomoxetine, sold under the brand name Strattera,[11] is a selective norepinephrine reuptake inhibitor (SNRI) medication used to treat attention deficit hyperactivity disorder (ADHD)[12] and, to a lesser extent, cognitive disengagement syndrome (CDS).[13][14][15] It may be used alone or along with psychostimulant medication.[16][17] It enhances the executive functions of self-motivation, sustained attention, inhibition, working memory, reaction time,[18] and emotional self-regulation.[19][20] Use of atomoxetine is only recommended for those who are at least six years old.[12] It is taken orally.[12] The effectiveness of atomoxetine is comparable to the commonly prescribed stimulant medication methylphenidate.[21][22][23][24]
Common side effects of atomoxetine include abdominal pain, decreased appetite, nausea, feeling tired, and dizziness.[12] Serious side effects may include angioedema, liver problems, stroke, psychosis, heart problems, suicide, and aggression.[12][25] There is a lack of data regarding its safety during pregnancy; as of 2019, its safety during pregnancy and for use during breastfeeding is not certain.[26][27]
It was approved for medical use in the United States in 2002.[12] In 2023, it was the 161st most commonly prescribed medication in the United States, with more than 3 million prescriptions.[28][29]
Medical uses
Atomoxetine is indicated for the treatment of attention deficit hyperactivity disorder (ADHD).[4]
Attention deficit hyperactivity disorder
Atomoxetine is approved for use in children, adolescents, and adults.[4] However, its efficacy has not been studied in children under six years old.[7] One of the primary differences with the standard stimulant treatments for ADHD is that it has little known abuse potential.[7] Meta-analyses and systematic reviews have found that atomoxetine has comparable efficacy and equal tolerability to methylphenidate in children and adolescents. In adults, efficacy and tolerability are equivalent.[21][22][23][24]
While its efficacy may be less than that of lisdexamfetamine,[30] there is some evidence supporting its use in combination with stimulants.[16] Doctors may prescribe non-stimulants including atomoxetine when a person has bothersome side effects from stimulants; when a stimulant was not effective; in combination with a stimulant to increase effectiveness;[31][32] when the cost of stimulants is prohibitive; or when there is concern about the abuse potential of stimulants in a patient with a history of substance use disorder.
Atomoxetine alleviates ADHD symptoms through norepinephrine reuptake inhibition and by indirectly increasing dopamine in the prefrontal cortex,[33] sharing 70–80% of the brain regions with stimulants in its produced effects.[34]
Unlike α2-adrenergic receptor agonists such as guanfacine and clonidine, atomoxetine’s use can be abruptly stopped without significant withdrawal symptoms being observed.[7]
The initial therapeutic effects of atomoxetine usually take 1 to 4 weeks to become apparent.[6][35][36] A further 2 to 4 weeks may be required for the full therapeutic effects to be seen.[37][35] Incrementally increasing response may occur up to 1 year or longer.[36][38] The maximum recommended total daily dose in children and adolescents is 70 mg and adults is 100 mg.
Atomoxetine (CAS# 83015-26-3) is a compound that appears in research chemical databases. Atomoxetine is a selective norepinephrine reuptake inhibitor (NRI) that is used for the treatment of attention deficit hyperactivity disorder (ADHD). However, specific information regarding its detailed biological activities is not readily available in the search results. It is intended for research use only and is not for human consumption.
| Targets |
Transporters fpr norepinephrine (NE), serotonin (5-HT) and dopamine (DA); SNRI/selective noradrenaline reuptake inhibitor
Atomoxetine targets the norepinephrine transporter (NET). By inhibiting NET, it increases the concentration of norepinephrine in the synaptic cleft. This enhances noradrenergic neurotransmission, which is thought to improve attention and reduce impulsivity and hyperactivity in ADHD. |
|---|---|
| ln Vitro |
The human heart sodium channel (hNav1.5) is interacting with tomoxetine (1-100 µM; 0.5-20 sec; tsA201 cells) in a state- and dose-dependent way [2].
Atomoxetine Hydrochloride is the hydrochloride salt of atomoxetine, a phenoxy-3-propylamine derivative and selective non-stimulant, norepinephrine reuptake inhibitor with cognitive-enhancing activity. Although its precise mechanism of action is unknown, atomoxetine appears to selectively inhibit the pre-synaptic norepinephrine transporter, resulting in inhibition of the presynaptic reabsorption of norepinephrine and prolongation of norepinephrine activity in the synaptic cleft. The effect on cognitive brain function may result in improved attention and decreased impulsivity and activity levels. |
| ln Vivo |
Tomoxetine (0.3-3 mg/kg; i.p.; 0-4 hours; male Sprague-Dawley rats) increases extracellular norepinephrine and dopamine 3-fold and increases intracellular Expression of Fos[1]. Tomoxetine (0.1-5 mg/kg; intraperitoneal injection and oral administration; for 14 days; spontaneously hypertensive rats) can improve ADHD-related behaviors in rats [3].
Atomoxetine (ATX) is a commonly used non-stimulant treatment for Attention deficit hyperactivity disorder (ADHD). It primarily acts to increase noradrenalin levels; however, at higher doses it can increase dopamine levels. To date there has been no investigations into the effects of orally-administered ATX in the most commonly used model of ADHD, the spontaneously hypertensive rat (SHR). The aim of this study was to describe the effects of doses thought to be selective (0.15 mg/kg) and non-selective (0.3 mg/kg) for noradrenalin on behavioural measures in the SHR. Firstly, we examined the effects of acute and chronic ATX on locomotor activity including sensitisation and cross-sensitisation to amphetamine. Secondly, we measured drug effects on impulsivity using a T-maze delay discounting paradigm. We found no effect of ATX on locomotor activity and no evidence for sensitisation or cross-sensitisation. Furthermore, there were no differences in T-maze performance, indicating no effects on impulsivity at these doses. The absence of behavioural sensitisation supports previous claims of superior safety relative to psychostimulants for the doses administered. There was also no effect on impulsivity; however, we suggest that was confounded by stress specific to SHRs. Implications for future studies, behavioural assessment of SHRs and their use as a model of ADHD are discussed[1]. |
| Enzyme Assay |
Atomoxetine, a neuroactive drug, is approved for the treatment of attention-deficit/hyperactivity disorder (ADHD). It is primarily known as a high affinity blocker of the noradrenaline transporter, whereby its application leads to an increased level of the corresponding neurotransmitter in different brain regions. However, the concentrations used to obtain clinical effects are much higher than those which are required to block the transporter system. Thus, off-target effects are likely to occur. In this way, we previously identified atomoxetine as blocker of NMDA receptors. As many psychotropic drugs give rise to sudden death of cardiac origin, we now tested the hypothesis whether atomoxetine also interacts with voltage-gated sodium channels of heart muscle type in clinically relevant concentrations. Electrophysiological experiments were performed by means of the patch-clamp technique at human heart muscle sodium channels (hNav1.5) heterogeneously expressed in human embryonic kidney cells. Atomoxetine inhibited sodium channels in a state- and use-dependent manner. Atomoxetine had only a weak affinity for the resting state of the hNav1.5 (Kr: ∼ 120 µM). The efficacy of atomoxetine strongly increased with membrane depolarization, indicating that the inactivated state is an important target. A hallmark of this drug was its slow interaction. By use of different experimental settings, we concluded that the interaction occurs with the slow inactivated state as well as by slow kinetics with the fast-inactivated state. Half-maximal effective concentrations (2-3 µM) were well within the concentration range found in plasma of treated patients. Atomoxetine also interacted with the open channel. However, the interaction was not fast enough to accelerate the time constant of fast inactivation. Nevertheless, when using the inactivation-deficient hNav1.5_I408W_L409C_A410W mutant, we found that the persistent late current was blocked half maximal at about 3 µM atomoxetine. The interaction most probably occurred via the local anesthetic binding site. Atomoxetine inhibited sodium channels at a similar concentration as it is used for the treatment of ADHD. Due to its slow interaction and by inhibiting the late current, it potentially exerts antiarrhythmic properties[2].
The activity of Atomoxetine can be assessed using radioligand binding assays with membranes expressing the norepinephrine transporter. The displacement of a radiolabeled NET ligand is measured to determine the binding affinity. Functional assays measuring the inhibition of norepinephrine uptake can also be used. |
| Cell Assay |
To evaluate the cellular effects of Atomoxetine, cells expressing NET are treated with the compound. The inhibition of norepinephrine uptake is measured.
|
| Animal Protocol |
Animal/Disease Models: Male SD (SD (Sprague-Dawley)) rat [1]
Doses: 0.3, 1 and 3 mg/kg Route of Administration: intraperitoneal (ip) injection; 4 hrs (hrs (hours)) Experimental Results: The number of cells expressing Fos-like immunoreactivity increased 3.7-fold in the PFC, extracellular Norepinephrine and dopamine increase 3-fold. Animal/Disease Models: Spontaneously hypertensive rat (SHR) [3] |
| ADME/Pharmacokinetics |
Absorption, Distribution and Excretion
The pharmacokinetic characteristics of atormoxetine are highly dependent on individual cytochrome P450 2D6 gene polymorphisms. A significant proportion of the population (up to 10% of Caucasians, 2% of African Americans, and 1% of Asians) are poor metabolizers (PMs) of CYP2D6-metabolized drugs. Compared to individuals with normal CYP2D6 activity, these individuals have reduced activity in this metabolic pathway, resulting in a 10-fold higher AUC, a 5-fold higher peak plasma concentration, and a slower elimination rate (plasma half-life of 21.6 hours). After oral administration, atormoxetine is rapidly absorbed, with an absolute bioavailability of approximately 63% in vigorous metabolizers (EMs) and approximately 94% in poor metabolizers (PMs). The mean maximum plasma concentration (Cmax) is reached approximately 1 to 2 hours after administration, with a maximum concentration of 350 ng/ml and an AUC of 2 mcg·h/ml. Atomoxetine is primarily excreted as 4-hydroxyatoromoxetine-O-glucuronide, mainly in the urine (over 80% of the dose) and a small amount in the feces (less than 17% of the dose). Only a small amount (less than 3%) of atoromoxetine is excreted unchanged, indicating extensive biotransformation. The volume of distribution (VOD) of orally administered atoromoxetine is 1.6–2.6 L/kg. The steady-state VOD of intravenously administered atoromoxetine is approximately 0.85 L/kg. The clearance of atoromoxetine depends on individual CYP2D6 gene polymorphism, ranging from 0.27–0.67 Lh/kg. Steady-state VOD (intravenous administration): 8.5 L/kg. Atomoxetine is primarily distributed in body fluids; after standardization to body weight, the VOD is similar among patients of different weights. Atomoxetine is rapidly absorbed after oral administration, with an absolute bioavailability of approximately 63% in fast metabolizers and approximately 94% in slow metabolizers. Maximum plasma concentration (Cmax) is reached approximately 1 to 2 hours after administration. /Milk/ Atomoxetine and/or its metabolites are distributed in rat milk; it is currently unknown whether the drug is distributed in human milk. …Atomoxetine has high water solubility and biomembrane permeability, enabling rapid and complete absorption after oral administration. Its absolute oral bioavailability ranges from 63% to 94%, primarily influenced by the degree of first-pass metabolism. Systemic clearance of atormoxetine involves three oxidative metabolic pathways: aromatic ring hydroxylation, benzylic hydroxylation, and N-demethylation. Aromatic ring hydroxylation produces the major oxidative metabolite of atormoxetine, 4-hydroxyatormoxetine, which is subsequently glucuronidated and excreted in the urine. The formation of 4-hydroxyatormoxetine is primarily mediated by the polymorphically expressed enzyme cytochrome P450 (CYP) 2D6. This results in two groups of individuals: those with high metabolic capacity (CYP2D6 fast metabolizers) and those with low metabolic capacity (CYP2D6 slow metabolizers). The oral bioavailability and clearance of atormoxetine are influenced by CYP2D6 activity; however, plasma pharmacokinetic parameters are predictable for both fast and slow metabolizers. Following a single oral dose, atormoxetine reaches peak plasma concentrations approximately 1–2 hours after administration. The plasma half-life is 5.2 hours for fast metabolizers and 21.6 hours for slow metabolizers. The systemic plasma clearance of atormoxetine is 0.35 L/h/kg for fast metabolizers and 0.03 L/h/kg for slow metabolizers. Correspondingly, the mean steady-state plasma concentration is approximately 10 times higher in slow metabolizers than in fast metabolizers. After multiple doses, atormoxetine accumulates in the plasma of slow metabolizers, while almost no accumulation occurs in fast metabolizers. The volume of distribution is 0.85 L/kg, indicating that atormoxetine is distributed in systemic water in both rapid and slow metabolizers. Atomoxetine is highly bound to plasma albumin (approximately 99% plasma binding). Although steady-state concentrations of atormoxetine are higher in slow metabolizers than in rapid metabolizers after administration of the same mg/kg/day dose, the frequency and severity of adverse events are similar regardless of CYP2D6 phenotype. Administration of atormoxetine does not inhibit or induce the clearance of other drugs metabolized by CYP enzymes. In rapid metabolizers, potent and selective CYP2D6 inhibitors reduce the clearance of atormoxetine. However, the use of CYP inhibitors in individuals with impaired metabolic capacity does not affect the steady-state plasma concentrations of atormoxetine. For more complete data on the absorption, distribution, and excretion of atormoxetine (8 drugs in total), please visit the HSDB record page. Metabolism/Metabolites |
| Toxicity/Toxicokinetics |
Toxicity Summary
Identification and Use: Atomoxetine (brand name: Strattera) is indicated for the treatment of attention deficit hyperactivity disorder (ADHD). Human Exposure and Toxicity: In short-term studies in children or adolescents with ADHD, atomoxetine increased the risk of suicidal ideation. Acute or chronic overdose of atomoxetine may be accompanied by gastrointestinal symptoms, somnolence, dizziness, tremor, behavioral abnormalities, hyperactivity, agitation, and signs and symptoms consistent with mild to moderate sympathetic nervous system activation (e.g., tachycardia, elevated blood pressure, dilated pupils, dry mouth). Less commonly, QT interval prolongation and altered mental status, including disorientation and hallucinations, have been reported. Atomoxetine may cause clinically significant hepatotoxicity through metabolic-specific reactions or by inducing autoimmune hepatitis. There have been reports of death resulting from combined overdose of atomoxetine (Stratera) and at least one other medication. Sudden death, stroke, and myocardial infarction have been reported in children and adults with structural heart abnormalities or other serious heart conditions. Animal studies: The estimated median lethal dose (LD50) of atormoxetine hydrochloride in animals via oral administration is: 25 mg/kg for cats, >37.5 mg/kg for dogs, and 0.190 mg/kg for rats and mice. Prodromal symptoms of atormoxetine toxicity following a single oral dose in animals include mydriasis and decreased pupillary light reflex, mucus in stool, salivation, vomiting, ataxia, tremor, myoclonus, and convulsions. Chronic toxicity studies were conducted in adult rats and dogs for up to one year. No major target organ toxicity was observed in dogs at oral doses up to 16 mg/kg/day, or in rats with a time-weighted average dose of up to 47 mg/kg/day when atormoxetine was added to their diet. These doses are 4–5 times the maximum recommended daily oral dose for adults. Mild hepatotoxicity was observed in male rats at a time-weighted average dose ≥14 mg/kg/day, manifested as mottled and pale liver, increased relative liver weight, hepatocyte vacuolation, and a slight increase in serum ALT levels. No hepatotoxicity was observed in dogs. Dogs exhibited clinical signs such as dilated pupils, decreased pupillary light reflex, vomiting, and tremors, but these symptoms were milder in adult dogs at daily doses ≥8 mg/kg. During organogenesis, oral administration of atormoxetine hydrochloride to rabbits and rats at doses up to 100 mg/kg/day and 150 mg/kg/day (13 times the maximum recommended daily oral dose for adults) did not reveal evidence of drug-related teratogenicity or fetal growth retardation. In a rat fertility study, decreased pup weight and survival were observed, primarily occurring in the first week postpartum, following a time-weighted average dose of atormoxetine ingested by the mother of 23 mg/kg/day or higher. Atomoxetine hydrochloride showed negative results in a series of genotoxicity studies, including the Ames test (reverse point mutation assay), in vitro mouse lymphoma assay, Chinese hamster ovary cell chromosomal aberration assay, rat hepatocyte unplanned DNA synthesis assay, and mouse in vivo micronucleus assay. However, a slight increase in the proportion of bichromosomal cells was observed in Chinese hamster ovary cells, suggesting internal duplication (chromosomal number abnormality). In rats and mice, no carcinogenicity was observed after two consecutive years of dietary administration of atormoxetine hydrochloride at a weighted average dose of up to 47 and 458 mg/kg/day, respectively. The exact mechanism of action of atormoxetine in treating attention deficit hyperactivity disorder (ADHD) is unclear, but in vitro studies suggest its action may be related to selective inhibition of presynaptic norepinephrine transporters. Atormoxetine appears to have very low affinity for other norepinephrine receptors or other neurotransmitter transporters or receptors. Interactions Atomoxetine should be used with caution in patients receiving systemic (oral or intravenous) salbutamol (or other β2-receptor agonists) therapy, as salbutamol may enhance cardiovascular effects, leading to increased heart rate and blood pressure. Salbutamol (600 mcg, intravenously, over 2 hours) can cause increased heart rate and blood pressure. Atomoxetine (60 mg twice daily for 5 days) enhances these effects, and is most pronounced after the first concurrent use of salbutamol and atomoxetine. However, another study in 21 healthy Asian subjects (excluded due to poor metabolic capacity) did not observe these effects on heart rate and blood pressure after concurrent inhalation of salbutamol (200-800 mcg) and atomoxetine (80 mg once daily for 5 days). The manufacturer states that atomoxetine is contraindicated in patients currently receiving or recently (within 2 weeks) receiving monoamine oxidase (MAO) inhibitor therapy. Furthermore, at least a 2-week interval should be maintained after discontinuing atomoxetine before initiating MAO inhibitor therapy. Patients receiving other medications that affect the concentration of monoamine neurotransmitters in the brain, especially when concurrently taking monoamine oxidase inhibitors (MAO inhibitors), have been reported to have experienced severe and even fatal reactions (including high fever, muscle rigidity, myoclonus, autonomic dysfunction with rapid fluctuations in vital signs, and altered mental status, such as extreme agitation, which can progress to delirium and coma). When atormoxetine is used concomitantly with drugs that inhibit the activity of the cytochrome P-450 2D6 (CYP2D6) isoenzyme, pharmacokinetic interactions may occur (slowing atormoxetine metabolism). CYP2D6 inhibitors can increase plasma atormoxetine concentrations in fast-metabolizing patients to levels similar to those in slow-metabolizing patients. When atormoxetine is used in combination with potent CYP2D6 inhibitors (such as paroxetine, fluoxetine, quinidine), or in patients with impaired CYP2D6 isoenzyme metabolism, the manufacturer recommends considering dose adjustments for atormoxetine. However, in vitro studies have shown that co-administration of atormoxetine with CYP2D6 inhibitors does not increase plasma atormoxetine concentrations in patients with impaired CYP2D6 metabolism. There may be potential drug interactions (enhanced hypertension) when atormoxetine is used co-administered with vasopressors (e.g., dopamine, dobutamine). Use with caution. For more complete data on drug interactions of atormoxetine (6 in total), please visit the HSDB record page. Atomoxetine can cause side effects such as nausea, dry mouth, insomnia, and increased heart rate. It may also cause suicidal ideation in children and adolescents. It should be used with caution and under medical supervision. |
| References |
|
| Additional Infomation |
Therapeutic Uses
Adrenergic Reuptake Inhibitors /Clinical Trials/ ClinicalTrials.gov is a registry and results database that lists human clinical studies funded by public and private institutions worldwide. The website is maintained by the National Library of Medicine (NLM) and the National Institutes of Health (NIH). Each record on ClinicalTrials.gov includes a summary of the study protocol, including: the disease or condition; the intervention (e.g., the medical product, behavior, or procedure under investigation); the title, description, and design of the study; participation requirements (eligibility criteria); the location of the study; contact information for the study location; and links to relevant information from other health websites, such as the NLM’s MedlinePlus (for providing patient health information) and PubMed (for providing citations and abstracts of academic articles in the medical field). Atomoxetine is listed in the database. Atomoxetine (Stratera) is indicated for the treatment of attention deficit hyperactivity disorder (ADHD). /Included in US Product Labelling/ /Exploratory Treatment/ /The purpose of this study is to/observe the efficacy and safety of atormoxetine hydrochloride in the treatment of childhood narcolepsy. This study included 66 patients with narcolepsy who met the diagnostic criteria of the International Classification of Sleep Disorders (ICSD-2) and received atormoxetine hydrochloride between November 2010 and December 2014. There were 42 males and 24 females, with a mean age of onset of 7.5 years (range 3.75–13.00 years) and a mean duration of illness of 1.75 years (range 0.25–5.00 years). Each patient underwent complete blood count, liver and kidney function tests, multiple sleep latency tests (MSLT), polysomnography (PSG), neuroimaging, and electroencephalography (EEG). Some children also underwent HLA-DR2 gene testing and serum infection marker testing. The 66 patients were followed up for 2 to 49 months (mean 18 months) to observe clinical efficacy and adverse reactions. Of the 62 patients, daytime sleepiness improved, with 11 (16.7%) showing improvement, 29 (43.9%) showing significant improvement, and 22 (33.3%) showing improvement. Of the 54 patients, sudden collapse occurred, with 18 (33.3%) showing improvement, 19 (35.2%) showing significant improvement, and 10 (18.5%) showing improvement. Of the 55 patients with nocturnal sleep disturbances, 47 showed symptom improvement, 14 (25.5%) had symptom control, 20 (36.4%) showed significant treatment efficacy, and 13 (23.6%) showed effective treatment. Thirteen patients experienced hypnagogic or waking hallucinations, with only 4 experiencing symptom control. Four patients developed sleep paralysis, with only 1 experiencing control. Eighteen patients showed improved attention and learning efficiency. Eighteen patients experienced anorexia, five experienced mood disorders, and two experienced depression. One patient each experienced nocturia, muscle tremors, and involuntary tongue movements. One patient experienced prolonged PR interval and premature atrial contractions. Atormoxetine hydrochloride is effective for excessive daytime sleepiness, cataplexy, and nocturnal sleep disturbances in patients with narcolepsy, but its efficacy against hallucinations and sleep paralysis is not significant. Adverse reactions are mild, with anorexia and mood disorders being relatively common. As a non-central nervous system stimulant, atomoxetine hydrochloride does not cause drug dependence and has no prescription restrictions; it is well-tolerated, safe, and effective, and can be considered a good alternative for the treatment of childhood narcolepsy. For more complete data on the therapeutic uses of atomoxetine (6 types), please visit the HSDB record page. Drug Warning |
| Molecular Formula |
C17H21NO
|
|---|---|
| Molecular Weight |
255.354744672775
|
| Exact Mass |
255.162
|
| Elemental Analysis |
C, 79.96; H, 8.29; N, 5.49; O, 6.27
|
| CAS # |
83015-26-3
|
| Related CAS # |
Atomoxetine hydrochloride;82248-59-7;(Rac)-Atomoxetine-d7 hydrochloride;Atomoxetine-d3 hydrochloride;1217776-38-9
|
| PubChem CID |
54841
|
| Appearance |
Typically exists as solid at room temperature
|
| Density |
1.0±0.1 g/cm3
|
| Boiling Point |
389.0±37.0 °C at 760 mmHg
|
| Melting Point |
161-165 ºC
|
| Flash Point |
164.1±16.0 °C
|
| Vapour Pressure |
0.0±0.9 mmHg at 25°C
|
| Index of Refraction |
1.552
|
| LogP |
3.28
|
| Hydrogen Bond Donor Count |
1
|
| Hydrogen Bond Acceptor Count |
2
|
| Rotatable Bond Count |
6
|
| Heavy Atom Count |
19
|
| Complexity |
237
|
| Defined Atom Stereocenter Count |
1
|
| SMILES |
[C@H](C1C=CC=CC=1)(CCNC)OC1C=CC=CC=1C
|
| InChi Key |
VHGCDTVCOLNTBX-QGZVFWFLSA-N
|
| InChi Code |
InChI=1S/C17H21NO/c1-14-8-6-7-11-16(14)19-17(12-13-18-2)15-9-4-3-5-10-15/h3-11,17-18H,12-13H2,1-2H3/t17-/m1/s1
|
| Chemical Name |
(3R)-N-methyl-3-(2-methylphenoxy)-3-phenylpropan-1-amine
|
| Synonyms |
Atomoxetine; 83015-26-3; Tomoxetine; (-)-Tomoxetine; Tomoxetina; Tomoxetinum; Strattera; Tomoxetinum [Latin];
|
| HS Tariff Code |
2934.99.9001
|
| Storage |
Powder -20°C 3 years 4°C 2 years In solvent -80°C 6 months -20°C 1 month |
| Shipping Condition |
Room temperature (This product is stable at ambient temperature for a few days during ordinary shipping and time spent in Customs)
|
| Solubility (In Vitro) |
May dissolve in DMSO (in most cases), if not, try other solvents such as H2O, Ethanol, or DMF with a minute amount of products to avoid loss of samples
|
|---|---|
| Solubility (In Vivo) |
Note: Listed below are some common formulations that may be used to formulate products with low water solubility (e.g. < 1 mg/mL), you may test these formulations using a minute amount of products to avoid loss of samples.
Injection Formulations
(e.g. IP/IV/IM/SC) Injection Formulation 1: DMSO : Tween 80: Saline = 10 : 5 : 85 (i.e. 100 μL DMSO stock solution → 50 μL Tween 80 → 850 μL Saline) View MoreInjection Formulation 4: DMSO : 20% SBE-β-CD in saline = 10 : 90 [i.e. 100 μL DMSO → 900 μL (20% SBE-β-CD in saline)] Oral Formulations
Oral Formulation 1: Suspend in 0.5% CMC Na (carboxymethylcellulose sodium) View MoreOral Formulation 3: Dissolved in PEG400
Note: Please be aware that the above formulations are for reference only. InvivoChem strongly recommends customers to read literature methods/protocols carefully before determining which formulation you should use for in vivo studies, as different compounds have different solubility properties and have to be formulated differently. (Please use freshly prepared in vivo formulations for optimal results.) |
| Preparing Stock Solutions | 1 mg | 5 mg | 10 mg | |
| 1 mM | 3.9162 mL | 19.5810 mL | 39.1619 mL | |
| 5 mM | 0.7832 mL | 3.9162 mL | 7.8324 mL | |
| 10 mM | 0.3916 mL | 1.9581 mL | 3.9162 mL |
*Note: Please select an appropriate solvent for the preparation of stock solution based on your experiment needs. For most products, DMSO can be used for preparing stock solutions (e.g. 5 mM, 10 mM, or 20 mM concentration); some products with high aqueous solubility may be dissolved in water directly. Solubility information is available at the above Solubility Data section. Once the stock solution is prepared, aliquot it to routine usage volumes and store at -20°C or -80°C. Avoid repeated freeze and thaw cycles.
- CAS No.
- 83015-26-3
- Chemical Name:
- (R)-Tomoxetine
- Synonyms
- Tomoxetine;(R)-N-methyl-3-phenyl-3-(o-tolyloxy)propan-1-amine;(3R)-N-methyl-3-(2-methylphenoxy)-3-phenylpropan-1-amine;HSDB7352;HSDB 7352;HSDB-7352;TomoxetineHcl;(r)-tomoxetine;(R)-Atomoxetine;(R)-Tomoxetine USP/EP/BP
- CBNumber:
- CB3378328
- Molecular Formula:
- C17H21NO
- Molecular Weight:
- 255.36
- MDL Number:
- MFCD06804608
- MOL File:
- 83015-26-3.mol
- MSDS File:
- SDS
- TDS File:
- TDS
| Product description | Number | Pack Size | Price |
| Atomoxetine ≥98% | 22248 | 5mg | $55 |
| Atomoxetine ≥98% | 22248 | 10mg | $99 |
| Atomoxetine 98.50% | CS-0028309 | 5mg | $162 |
| Atomoxetine 98.50% | CS-0028309 | 10mg | $260 |
| Atomoxetine 98.50% | CS-0028309 | 25mg | $520 |
| More product size | |||
| Boiling point | 389.0±37.0 °C(Predicted) |
|---|---|
| Density | 1.023±0.06 g/cm3(Predicted) |
| pka | 10.15±0.10(Predicted) |
| CAS DataBase Reference | 83015-26-3(CAS DataBase Reference) |
| FDA UNII | ASW034S0B8 |
SAFETY
Risk and Safety Statements
| Symbol(GHS) |     GHS08,GHS09,GHS05,GHS06 |
|---|---|
| Signal word | Danger |
| Hazard statements | H318-H411-H301-H331-H361 |
| Precautionary statements | P261-P271-P304+P340-P311-P321-P403+P233-P405-P501-P264-P270-P301+P310-P321-P330-P405-P501-P280-P305+P351+P338-P310-P201-P202-P281-P308+P313-P405-P501 |
| Safety Statements | 22-24/25 |
| Hazardous Substances Data | 83015-26-3(Hazardous Substances Data) |
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
Buy Atomoxetine (Strattera) Cas 83015-26-3
(R)-Tomoxetine price More Price(17)
| Manufacturer | Product number | Product description | CAS number | Packaging | Price | Updated | Buy |
|---|---|---|---|---|---|---|---|
| Cayman Chemical | 22248 | Atomoxetine ≥98% | 83015-26-3 | 5mg | $55 | 2021-12-16 | Buy |
| Cayman Chemical | 22248 | Atomoxetine ≥98% | 83015-26-3 | 10mg | $99 | 2021-12-16 | Buy |
| ChemScene | CS-0028309 | Atomoxetine 98.50% | 83015-26-3 | 5mg | $162 | 2026-06-04 | Buy |
| ChemScene | CS-0028309 | Atomoxetine 98.50% | 83015-26-3 | 10mg | $260 | 2026-06-04 | Buy |
| ChemScene | CS-0028309 | Atomoxetine 98.50% | 83015-26-3 | 25mg | $520 | 2026-06-04 | Buy |
(R)-Tomoxetine Chemical Properties, Uses, Production
Synthesis
1. 
Figure 1 shows the synthetic route 1 of (R)-Tomoxetine.
This route does not consider the optical rotation of (R)-Tomoxetine, resulting in a low yield. The final step of the reaction requires N-demethylation, and the demethylating reagent used is highly toxic, leading to a low reaction yield. Furthermore, the chlorination of the amino alcohol also generates dehydration products.
2. 
Figure 2 shows the second synthetic route of (R)-Tomoxetine.
This route employs asymmetric synthesis catalyzed by chemical enzymes, using ethyl benzophthaloacetate as the precursor. The target product with optical purity is obtained through six steps, resulting in a relatively high overall yield. However, the price of chemical enzymes is high, which is a consideration for economic efficiency.
3. 
Figure 3 shows the synthetic route 3 of (R)-Tomoxetine.
This synthetic route involves six steps: Mannich reaction, reduction, chlorination, etherification, resolution, and demethylation, yielding the target product. The operation is simple, the reaction conditions are mild, and the yield is relatively high. However, the cited literature is a patent and is subject to copyright restrictions.
4. 
Figure 4 shows the synthetic route 4 of (R)-Tomoxetine.
Uses
(R)-Tomoxetine is a compound active at novel site on receptor-operated calcium channels useful for treatment of neurological disorders and diseases.
Definition
(R)-Tomoxetine is a secondary amino compound having methyl and 3-(2-methylphenoxy)-3-phenylpropan-1-yl substituents.
brand name
Strattera (Lilly).
- CAS No.
- 83015-26-3
- Chemical Name:
- (R)-Tomoxetine
- Synonyms
- Tomoxetine;(R)-N-methyl-3-phenyl-3-(o-tolyloxy)propan-1-amine;(3R)-N-methyl-3-(2-methylphenoxy)-3-phenylpropan-1-amine;HSDB7352;HSDB 7352;HSDB-7352;TomoxetineHcl;(r)-tomoxetine;(R)-Atomoxetine;(R)-Tomoxetine USP/EP/BP
- CBNumber:
- CB3378328
- Molecular Formula:
- C17H21NO
- Molecular Weight:
- 255.36
- MDL Number:
- MFCD06804608
- MOL File:
- 83015-26-3.mol
- MSDS File:
- SDS
- TDS File:
- TDS
| Product description | Number | Pack Size | Price |
| Atomoxetine ≥98% | 22248 | 5mg | $55 |
| Atomoxetine ≥98% | 22248 | 10mg | $99 |
| Atomoxetine 98.50% | CS-0028309 | 5mg | $162 |
| Atomoxetine 98.50% | CS-0028309 | 10mg | $260 |
| Atomoxetine 98.50% | CS-0028309 | 25mg | $520 |
| More product size | |||
| Boiling point | 389.0±37.0 °C(Predicted) |
|---|---|
| Density | 1.023±0.06 g/cm3(Predicted) |
| pka | 10.15±0.10(Predicted) |
| CAS DataBase Reference | 83015-26-3(CAS DataBase Reference) |
| FDA UNII | ASW034S0B8 |
SAFETY
Risk and Safety Statements
| Symbol(GHS) | GHS08,GHS09,GHS05,GHS06 |
|---|---|
| Signal word | Danger |
| Hazard statements | H318-H411-H301-H331-H361 |
| Precautionary statements | P261-P271-P304+P340-P311-P321-P403+P233-P405-P501-P264-P270-P301+P310-P321-P330-P405-P501-P280-P305+P351+P338-P310-P201-P202-P281-P308+P313-P405-P501 |
| Safety Statements | 22-24/25 |
| Hazardous Substances Data | 83015-26-3(Hazardous Substances Data) |
(R)-Tomoxetine price More Price(17)
| Manufacturer | Product number | Product description | CAS number | Packaging | Price | Updated | Buy |
|---|---|---|---|---|---|---|---|
| Cayman Chemical | 22248 | Atomoxetine ≥98% | 83015-26-3 | 5mg | $55 | 2021-12-16 | Buy |
| Cayman Chemical | 22248 | Atomoxetine ≥98% | 83015-26-3 | 10mg | $99 | 2021-12-16 | Buy |
| ChemScene | CS-0028309 | Atomoxetine 98.50% | 83015-26-3 | 5mg | $162 | 2026-06-04 | Buy |
| ChemScene | CS-0028309 | Atomoxetine 98.50% | 83015-26-3 | 10mg | $260 | 2026-06-04 | Buy |
| ChemScene | CS-0028309 | Atomoxetine 98.50% | 83015-26-3 | 25mg | $520 | 2026-06-04 | Buy |
(R)-Tomoxetine Chemical Properties, Uses, Production
Synthesis
1.
Figure 1 shows the synthetic route 1 of (R)-Tomoxetine.
This route does not consider the optical rotation of (R)-Tomoxetine, resulting in a low yield. The final step of the reaction requires N-demethylation, and the demethylating reagent used is highly toxic, leading to a low reaction yield. Furthermore, the chlorination of the amino alcohol also generates dehydration products.
2.
Figure 2 shows the second synthetic route of (R)-Tomoxetine.
This route employs asymmetric synthesis catalyzed by chemical enzymes, using ethyl benzophthaloacetate as the precursor. The target product with optical purity is obtained through six steps, resulting in a relatively high overall yield. However, the price of chemical enzymes is high, which is a consideration for economic efficiency.
3.
Figure 3 shows the synthetic route 3 of (R)-Tomoxetine.
This synthetic route involves six steps: Mannich reaction, reduction, chlorination, etherification, resolution, and demethylation, yielding the target product. The operation is simple, the reaction conditions are mild, and the yield is relatively high. However, the cited literature is a patent and is subject to copyright restrictions.
4.
Figure 4 shows the synthetic route 4 of (R)-Tomoxetine.
Uses
(R)-Tomoxetine is a compound active at novel site on receptor-operated calcium channels useful for treatment of neurological disorders and diseases.
Definition
(R)-Tomoxetine is a secondary amino compound having methyl and 3-(2-methylphenoxy)-3-phenylpropan-1-yl substituents.
brand name
Strattera (Lilly).
in vivo
Atomoxetine (Tomoxetine) (0.3-3 mg/kg; i.p.; 0-4 hours; male Sprague-Dawley rats) increases extracellular norepinephrine and dopamine by 3-fold and increases Fos expression in the rat prefrontal cortex[1].
Atomoxetine (Tomoxetine) (0.1-5 mg/kg; i.p. and p.o; for 14 days; spontaneously hypertensive rat) can improve behaviors associated with ADHD in rats[3].
| Animal Model: | Male Sprague-Dawley rats[1] |
| Dosage: | 0.3, 1 and 3 mg/kg |
| Administration: | Intraperitoneal injection; for 4 hours |
| Result: | Increased the number of cells expressing Fos-like immunoreactivity in PFC 3.7-fold and increased extracellular norepinephrine and dopamine by 3-fold. |
| Animal Model: | Spontaneously hypertensive rat (SHR)[3] |
| Dosage: | 0.1, 0.3, 1.25 and 5.0 mg/kg |
| Administration: | Intraperitoneal injection and oral administration; for 14 days |
| Result: | Had non-impact on the measurement of motor activity. |
- Buy High-Quality R-(-)-Atomoxetine from Simson Pharma Limited at best competitive price.
- Every compound produced by Simson Pharma is accompanied by Certificate of Analysis.
Product Applications & Regulatory Search Terms:
Buy 83015-26-3 | Purchase 83015-26-3 | Order 83015-26-3 | Enquire 83015-26-3 | Price of 83015-26-3 | 83015-26-3 Supplier | 83015-26-3 Manufacturer | 83015-26-3 Exporter | R-(-)-Atomoxetine for Method Validation | R-(-)-Atomoxetine Reference Standard | R-(-)-Atomoxetine for ANDA Filing | R-(-)-Atomoxetine for Forced Degradation Studies | R-(-)-Atomoxetine Identification Standards | R-(-)-Atomoxetine for DMF Filing | Buy high quality R-(-)-Atomoxetine | Purchase R-(-)-Atomoxetine | R-(-)-Atomoxetine suppliers | R-(-)-Atomoxetine manufacturers | R-(-)-Atomoxetine price | R-(-)-Atomoxetine exporter | Order R-(-)-Atomoxetine | Enquire R-(-)-Atomoxetine | R-(-)-Atomoxetine cost | R-(-)-Atomoxetine Supplier | R-(-)-Atomoxetine Distributor
(R)-Tomoxetine Preparation Products And Raw materials
Raw materials
Preparation Products
Atomoxetine (Tomoxetine) (0.3-3 mg/kg; i.p.; 0-4 hours; male Sprague-Dawley rats) increases extracellular norepinephrine and dopamine by 3-fold and increases Fos expression in the rat prefrontal cortex[1].
Atomoxetine (Tomoxetine) (0.1-5 mg/kg; i.p. and p.o; for 14 days; spontaneously hypertensive rat) can improve behaviors associated with ADHD in rats[3].
| Animal Model: | Male Sprague-Dawley rats[1] |
| Dosage: | 0.3, 1 and 3 mg/kg |
| Administration: | Intraperitoneal injection; for 4 hours |
| Result: | Increased the number of cells expressing Fos-like immunoreactivity in PFC 3.7-fold and increased extracellular norepinephrine and dopamine by 3-fold. |
| Animal Model: | Spontaneously hypertensive rat (SHR)[3] |
| Dosage: | 0.1, 0.3, 1.25 and 5.0 mg/kg |
| Administration: | Intraperitoneal injection and oral administration; for 14 days |
| Result: | Had non-impact on the measurement of motor activity. |
(R)-Tomoxetine Preparation Products And Raw materials
Raw materials
Preparation Products
-
Atomoxetine | CAS 83015-26-3 | SoleChem
Atomoxetine Supplier — CAS 83015-26-3, also supplied as Atomoxetine HCl salt. API and reference standard grades available for …
-
R- (-)-Atomoxetine | CAS No- 83015-26-3 | Simson Pharma Limited
Buy High-Quality R- (-)-Atomoxetine from Simson Pharma Limited at best competitive price. Every compound produced by Simson …
Atomoxetine | CAS 83015-26-3 | TargetMol | Biomol.com
Buy Atomoxetine, CAS: 83015-26-3, item number: TGM-T20886-25mg from TargetMol at Biomol!
-
Atomoxetine | 83015-26-3 – Chemicea
Buy high quality Atomoxetine from Chemicea Pharmaceuticals. Chemicea Pharmaceuticals is one of the leading manufacturer and …
Atomoxetine | CS-O-11086 | CAS 83015-26-3 | Clearsynth
Buy Atomoxetine from Clearsynth. View CAT No. CS-O-11086, CAS No. 83015-26-3, molecular formula, molecular weight, stock …
-
(R)-Tomoxetine | 83015-26-3 – ChemicalBook
Jul 17, 2026 · (R)-Tomoxetine (CAS 83015-26-3) information, including chemical properties, structure, melting point, boiling point, …
-
Atomoxetine | CAS No: 83015-26-3 – aquigenbio.com
Buy high quality Atomoxetine, CAS No: 83015-26-3 from AquigenBio, the leading Pharmaceutical Impurities Manufacturer and Supplier.
-
Atomoxetine | inhibitor of noradrenaline | CAS# 83015-26-3 | InvivoChem
Atomoxetine (Tomoxetine) is a potent Na+ channel blocker (VGSCs). Atomoxetine (Tomoxetine) may be utilized in study/research of …
Atomoxetine | CAS#83015-26-3 | noradrenaline inhibitor | MedKoo
Atomoxetine is a norepinephrine reuptake inhibitor approved for the treatment of attention deficit hyperactivity disorder (ADHD). The …
-
Atomoxetine | Noradrenaline Reuptake Inhibitor | 83015-26-3 | AdooQ®
Atomoxetine is a selective noradrenaline reuptake inhibitor primarily targeting norepinephrine transporters with Ki values of 5 nM. It is …
Reviews
There are no reviews yet.